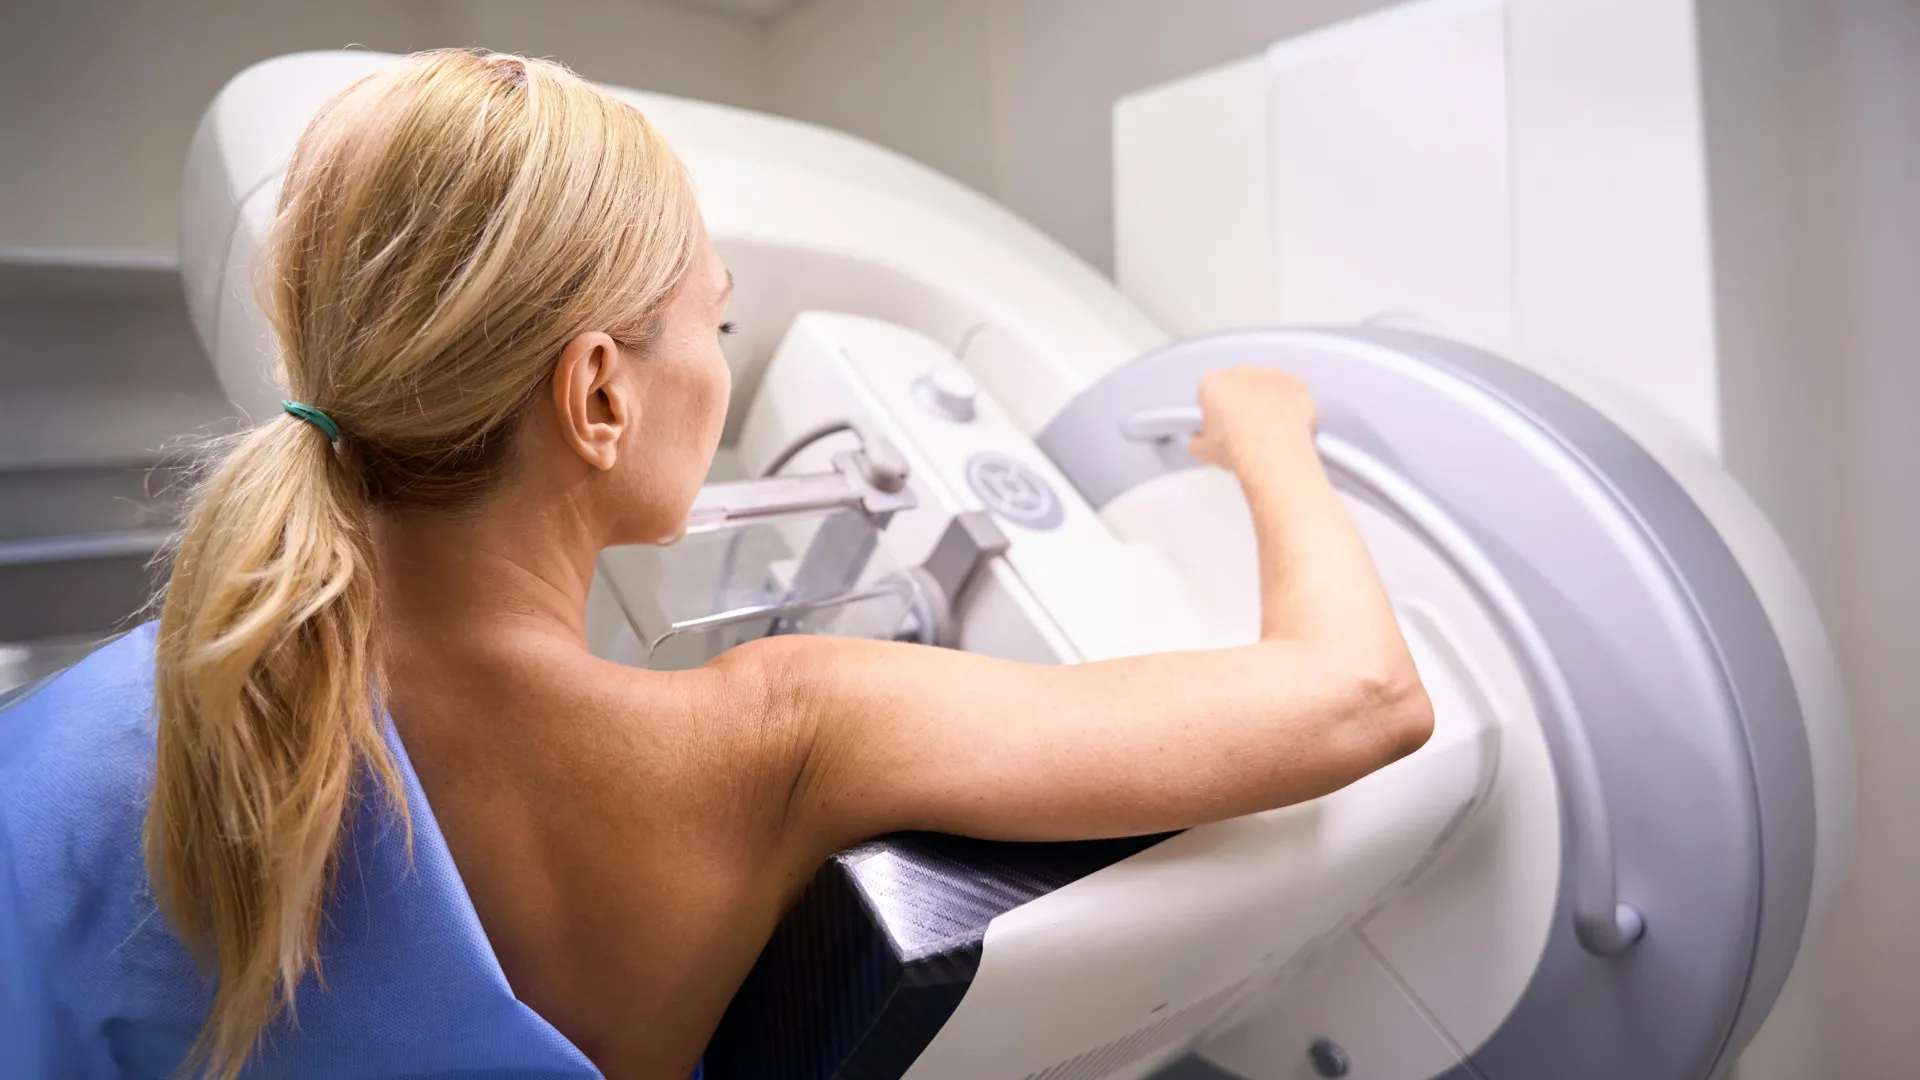
For decades, the efficacy of population-based mammography screening programs has been a subject of intense scientific and public discussion, often overshadowed by concerns regarding the phenomenon known as overdiagnosis. This particular challenge arises when medical imaging identifies a malignancy that, left undetected, would never have progressed to cause symptoms, threaten a woman’s health, or shorten her lifespan. Historically, estimates suggested that a significant proportion — potentially ranging from 30% to 50% — of all breast cancers identified through screening might fall into this category, casting a long shadow over the perceived net benefits of early detection initiatives. These substantial figures have permeated international health policy debates, influenced clinical guidelines, and often fueled public apprehension, leading many women to weigh the benefits of early cancer detection against the very real possibility of unnecessary treatment for a harmless lesion.
The implications of overdiagnosis extend far beyond mere statistical anomalies; they impact individuals on a deeply personal level. A diagnosis of breast cancer, even one that would prove harmless, can trigger profound psychological distress, anxiety, and a cascade of medical interventions. Women identified with such non-progressive cancers often undergo biopsies, surgeries, radiation therapy, and sometimes even chemotherapy, all of which carry their own risks, side effects, and financial burdens, without any actual improvement in their long-term health or survival. This ethical quandary has placed healthcare providers in a difficult position, necessitating a delicate balance when communicating the potential advantages of screening alongside its inherent drawbacks. The previous high overdiagnosis estimates thus presented a formidable challenge to the widespread acceptance and optimal implementation of screening programs designed to save lives.
However, a groundbreaking multinational research collaboration has now offered a comprehensive re-evaluation, suggesting that the true prevalence of overdiagnosis in breast cancer screening may be considerably lower than previously assumed. This pivotal study, spearheaded by researchers from institutions including the University of Southern Denmark, Lillebælt Hospital, the University of Copenhagen, and Queen Mary University of London, aimed to consolidate and rigorously re-analyze all available evidence from randomized controlled trials. Their objective was to achieve a clearer, more accurate understanding of overdiagnosis, thereby providing a more realistic framework for interpreting the benefits and harms associated with population-level mammography programs.
To achieve this revised understanding, the research team embarked on an exhaustive meta-analysis, systematically combining and re-examining data from all eight major randomized controlled trials of mammography screening ever conducted. These landmark studies, including the New York Health Insurance Plan, Malmö, Two-County, Edinburgh, the Canadian National Breast Screening Study, Stockholm, Gothenburg, and UK Age trials, collectively represent decades of research and thousands of participants. The researchers focused their analysis on both invasive breast cancer and ductal carcinoma in situ (DCIS), a non-invasive condition often considered a precursor to invasive cancer, whose detection through screening frequently contributes to overdiagnosis figures. The strength of this meta-analytic approach lies in its ability to synthesize disparate findings, overcome the limitations of individual studies, and provide a more statistically robust estimate of the overall effect.
A critical component of this innovative methodology involved calibrating the re-analyzed trial data against real-world observations from Denmark. The Danish experience provided a uniquely valuable reference point due to the staggered introduction of organized breast cancer screening programs across its regions. Some areas initiated screening up to 17 years earlier than others, effectively creating a natural experiment. This temporal difference allowed researchers to meticulously track the evolution of breast cancer diagnoses immediately following the introduction of screening and observe how these patterns unfolded over extended periods. By comparing incidence trends in the randomized trials with these empirically observed patterns in Denmark, the team could assess the consistency of the data and gain crucial insights into the underlying dynamics of diagnosis rates.
A central revelation of the study revolves around the profound impact of "timing effects" on overdiagnosis estimates. When a population-wide screening program is launched, there is an immediate and noticeable surge in breast cancer diagnoses. This initial increase occurs because screening technologies, such as mammography, can detect cancers earlier than they would have been found through symptoms or routine clinical examination. This phenomenon is often referred to as lead time bias. Crucially, as Professor Emerita Elsebeth Lynge from the Department of Public Health, University of Copenhagen, explained, this early detection should, over time, be followed by a corresponding drop in diagnoses, as many of these cancers would have eventually surfaced even without screening, just at a later stage. "When screening is introduced, the number of breast cancer diagnoses initially rises because cancers are detected earlier than they would have been without screening," she stated. "Over time, this should be followed by a drop, as some of these cancers would otherwise have been diagnosed later. If researchers do not take these factors into account, the initial increase can be mistaken for overdiagnosis." This nuanced understanding of incidence patterns over time is paramount to distinguishing true overdiagnosis from merely earlier detection.
The new analysis revealed that many earlier estimates of overdiagnosis were likely skewed by methodological limitations, particularly the duration of follow-up in the original trials. If a study concludes before enough time has elapsed for the post-screening drop in diagnoses to become apparent, the initial surge can be erroneously interpreted as an excess of overdiagnosed cases. Furthermore, estimates can be distorted if women originally assigned to control groups in these trials later accessed screening services themselves, effectively "contaminating" the control arm and blurring the distinction between screened and unscreened populations. Senior Epidemiologist Matejka Rebolj from Queen Mary University of London underscored this point, noting, "Taken together, we believe some previous high estimates of overdiagnosis, which influenced screening guidelines and communication, were based on evidence before trial data had fully matured. When interpreted in their full temporal context, randomized trial data are consistent with overdiagnosis of less than five percent, rather than with estimates nearing 50%." This re-evaluation of the temporal context proved instrumental in adjusting the perceived scale of the problem.
The revised figures represent a dramatic shift in understanding. The researchers concluded that when these critical factors — screening exposure differences and sufficient follow-up time — are appropriately accounted for, the extent of overdiagnosis in breast cancer screening is likely below 5%. This stands in stark contrast to the frequently cited figures of 30-50%, fundamentally altering the risk-benefit calculus for mammography. The consistency between the re-analyzed randomized trial data and the long-term patterns observed in Denmark’s routine screening programs lends substantial credibility to this significantly lower estimate. This finding suggests that the vast majority of cancers detected through screening are indeed clinically significant and would eventually have caused harm if left untreated.
For women considering or participating in breast cancer screening programs, these findings offer substantial reassurance. Understanding the true balance between the benefits of early detection and the potential downsides of overdiagnosis is crucial for making informed health decisions. As Professor Sisse Helle Njor from the University of Southern Denmark and Lillebælt Hospital articulated, "Most women will not develop breast cancer, but with this study we can now be reassured that the benefits of detecting breast cancer early and preventing premature death will outweigh the small risk of unnecessary treatment." This new evidence empowers women with a more accurate perspective, allowing them to approach screening decisions with greater confidence that the intervention is predominantly beneficial.
The implications of this study extend beyond individual patient counseling, potentially reshaping public health policy and communication strategies globally. National and international health organizations may now revisit their screening guidelines, emphasizing the profound life-saving benefits of early detection with a more accurate and reassuring understanding of overdiagnosis risks. This revised evidence provides a robust framework for healthcare professionals to better inform women when they are invited for screening, fostering greater trust and participation in programs designed to reduce breast cancer mortality. By clarifying the true extent of overdiagnosis, the study helps to refocus the narrative on the significant positive impact of screening.
While this research provides a significant recalibration, the scientific community’s quest for optimizing breast cancer screening continues. Future studies may delve into personalized screening approaches, explore novel biomarkers to differentiate aggressive cancers from indolent ones, or refine risk stratification models. Nevertheless, this comprehensive re-analysis marks a pivotal moment, offering a more precise and optimistic outlook on the balance of benefits and harms in breast cancer screening. It reinforces the critical role of mammography as a vital public health tool, capable of detecting life-threatening cancers early while minimizing the concern of identifying those that pose no genuine threat.
This research was made possible through dedicated support, with Casper Urth Pedersen receiving funding from the Novo Nordisk Foundation (reference: NNF22OC0076184) and Matejka Rebolj supported by Cancer Research UK (reference: C8162/A29083).
About the Author