The landscape of cancer treatment is continually evolving, with immunotherapy emerging as a powerful weapon against various malignancies. Among these innovative approaches, T-cell receptor (TCR) therapy holds significant promise, particularly for challenging solid tumors. This advanced form of cellular therapy genetically modifies a patient’s own immune cells, known as T cells, to precisely identify and eradicate cancerous cells. However, its widespread application has been hampered by formidable obstacles, including the need for individualized production, prohibitively high costs, and the risk of severe side effects when using donor cells. Recent groundbreaking research from a team at the University of California, Los Angeles (UCLA), published in Cell Reports Medicine, presents a novel strategy that could circumvent these limitations, potentially ushering in an era of readily available, "off-the-shelf" T-cell therapies derived from donated umbilical cord blood.
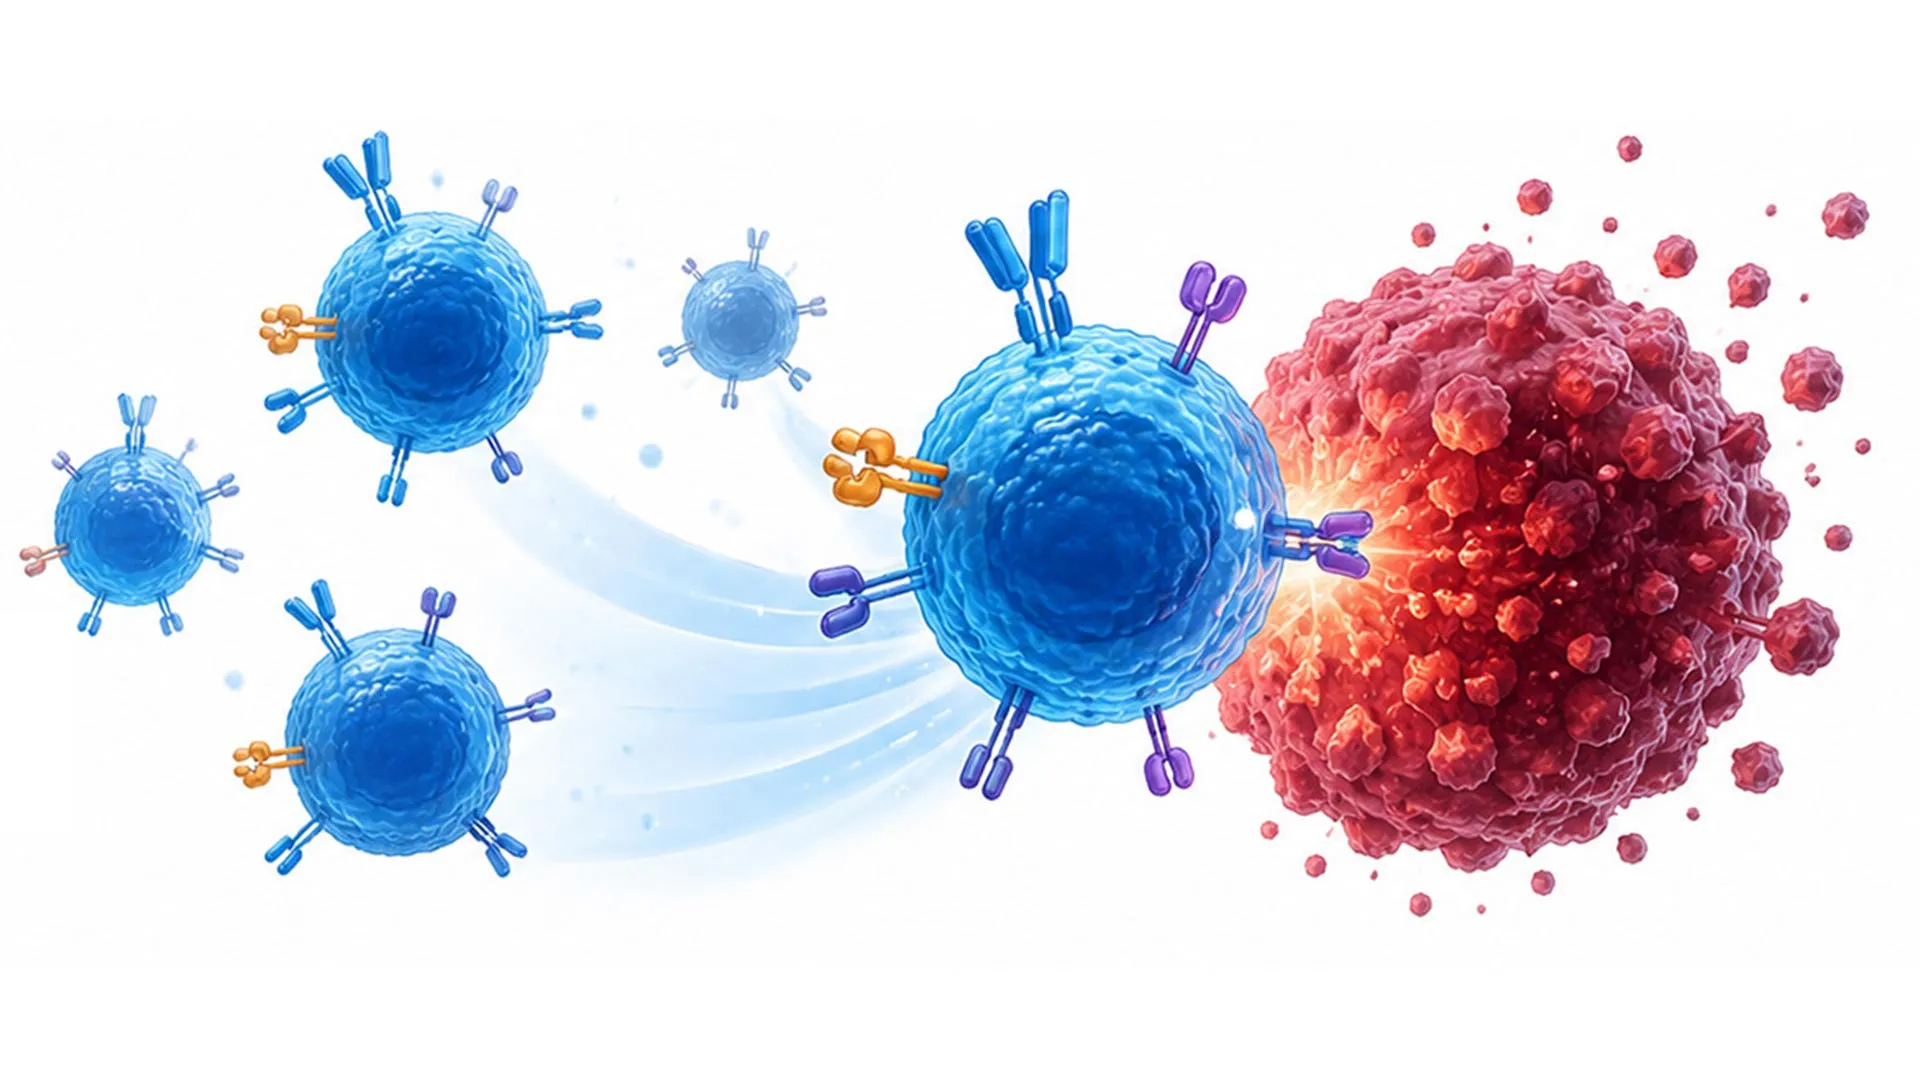
Traditional T-cell immunotherapies, such as CAR T-cell therapy, typically target proteins located on the exterior surface of cancer cells. While effective for certain blood cancers, this approach often falls short when confronted with solid tumors. Many of the critical molecular alterations that drive the cancerous transformation of solid tumor cells are situated deep within the cell’s interior. These internal proteins, when broken down into smaller fragments, can be presented on the cell surface as identifying tags by specialized molecules. TCR therapy possesses the unique capability to recognize these internal protein fragments, allowing it to penetrate beyond the surface-level recognition of other immunotherapies. This expanded reach is crucial for tackling the complexities of solid tumors, where many oncogenic drivers remain inaccessible to current treatments.
Despite this profound therapeutic potential, the practical implementation of TCR therapy has faced substantial hurdles. Current methods necessitate the creation of a bespoke treatment for each individual patient, utilizing their own T cells. This labor-intensive process can extend over several weeks, leading to significant delays for patients whose conditions demand urgent intervention. Furthermore, the manufacturing costs associated with such highly personalized therapies can escalate well into the hundreds of thousands of dollars, making them inaccessible to a large segment of the patient population.
An alternative under investigation involves developing allogeneic, or "universal," T-cell therapies from healthy donors. The vision is to produce batches of therapeutic cells in advance, store them, and administer them to multiple patients as needed. While offering a solution to scalability, this approach introduces a critical safety concern: graft-versus-host disease (GvHD). In GvHD, the transplanted donor immune cells perceive the patient’s healthy tissues as foreign and mount an attack, leading to potentially life-threatening complications. Overcoming this immune rejection while ensuring therapeutic efficacy has been a persistent challenge in the field of allogeneic cell therapy.
The UCLA researchers, led by co-senior authors Lili Yang, a professor of microbiology, immunology, and molecular genetics and a member of the UCLA Broad Stem Cell Research Center and the UCLA Health Jonsson Comprehensive Cancer Center, and Yanruide (Charlie) Li, a postdoctoral scholar in the Yang lab, have devised an ingenious strategy that simultaneously addresses the manufacturing bottleneck and the risk of GvHD. Their innovation lies in starting the therapeutic cell production process at a much earlier stage of immune cell development, utilizing blood stem cells sourced from donated umbilical cord blood.
Umbilical cord blood is a rich reservoir of hematopoietic stem cells, which possess the remarkable ability to differentiate into all major types of blood and immune cells. By beginning with these immature stem cells, the UCLA team was able to genetically engineer them with a receptor designed to recognize NY-ESO-1, a specific protein antigen frequently expressed across a wide spectrum of solid tumors. Crucially, this engineering step occurs before the cells mature into T cells.
As co-first author Yichen (John) Zhu, a graduate student in the UCLA Broad Stem Cell Research Center Training Program, explained, "Stem cells are undifferentiated – they’re not yet mature T cells with a fixed receptor already in place. When we differentiate our engineered stem cells into T cells, essentially all of the resulting cells carry the same receptor and go after the same tumor target." This early-stage genetic modification offers a distinct advantage over using mature donor T cells. Unlike mature donor T cells, which possess a diverse array of pre-existing natural T-cell receptors that could trigger GvHD, the stem cell-derived T cells develop with a uniform, engineered receptor. This homogeneity significantly reduces the likelihood of the therapeutic cells attacking healthy patient tissues, thereby mitigating the risk of GvHD without requiring extensive additional gene editing to silence endogenous receptors. After genetic modification, these engineered stem cells are then guided in the laboratory to mature into fully functional, cancer-targeting T cells.
Beyond addressing scalability and safety, the UCLA team also tackled another significant challenge in solid tumor therapy: antigen escape. Solid tumors are notoriously heterogeneous, meaning that cancer cells within the same tumor can exhibit considerable genetic and phenotypic diversity. Some tumor cells may cease to display the specific molecular marker that a targeted therapy is designed to recognize, a phenomenon known as antigen escape. When this occurs, the therapy loses its effectiveness, allowing resistant cancer cells to survive and the disease to recur.
To counter this, the engineered T cells, dubbed AlloESO-T cells, were designed with a dual detection system. In addition to the primary engineered receptor targeting NY-ESO-1, these cells also carry natural killer (NK) cell receptors. NK cell receptors are adept at recognizing general "stress signals" displayed by many tumor cells, irrespective of their specific antigen expression. This built-in redundancy means that even if a tumor cell manages to downregulate or hide its NY-ESO-1 antigen, the AlloESO-T cells may still be able to detect and eliminate it through the NK cell receptor pathway. "Solid tumors are very diverse," Zhu reiterated. "Some tumor cells lose or hide the antigen a therapy is designed to find – what we call antigen escape. When that happens, a therapy built around a single target loses its grip. Our stem cell-derived cells still have a second mechanism to kill those tumor cells." Laboratory experiments using human melanoma, ovarian, and prostate cancer cell lines confirmed this premise, demonstrating that the natural killer receptors enabled the engineered T cells to destroy cancer cells that were otherwise resistant to elimination via the NY-ESO-1 targeting pathway alone. This dual-targeting mechanism offers a robust defense against antigen escape, potentially enhancing the durability of the therapeutic response.
Preclinical evaluations of the AlloESO-T cells in mouse models of ovarian cancer and melanoma yielded highly encouraging results. A single dose of the engineered cells demonstrated prolonged tumor control and significantly extended survival in mice with ovarian cancer. In contrast, control groups receiving conventionally engineered T cells derived from mature donor cells experienced only partial tumor control and, crucially, developed symptoms of graft-versus-host disease. Similar positive outcomes were observed in the melanoma model, where AlloESO-T cells effectively slowed tumor progression and delayed recurrence, outperforming conventional comparison cells that provided only temporary control.
Further analysis revealed stark differences in the in vivo behavior of the two cell types. Following a single infusion, the AlloESO-T cells exhibited remarkable expansion, increasing in number by approximately 100-fold. They efficiently migrated into tumor sites, proliferated where needed, and maintained their anti-tumor activity for weeks, all while largely sparing healthy organs. The conventionally engineered donor T cells, conversely, showed undesirable accumulation in the liver and lungs, leading to the systemic toxicity that the new stem cell-based strategy aims to prevent.
Beyond the impressive anti-tumor efficacy and safety profile, one of the most transformative aspects of this platform is its manufacturing potential. The personalized nature of current T-cell treatments necessitates individual cell collection and processing for each patient, a model that is inherently difficult to scale. By initiating the process with cord blood stem cells, researchers can produce therapeutic cells on an industrial scale. A relatively small initial quantity of cord blood stem cells has the capacity to generate an enormous number of immune cells. As Li emphasized, "From a small number of cord blood stem cells, we can generate trillions of therapeutic cells – enough for thousands of doses – within about six weeks." This unprecedented scalability has profound implications for accessibility, as the estimated cost per dose of this approach is dramatically lower than current personalized T-cell therapies, potentially reducing it from hundreds of thousands of dollars to an estimated $5,000.
The UCLA researchers envision the AlloESO-T system as more than just a therapy for a single cancer protein; they see it as a versatile platform. Many solid tumors currently lack suitable surface proteins for recognition by conventional immune therapies. TCR-based treatments, with their ability to identify internal protein fragments displayed on the cell surface, offer a pathway to target these previously intractable cancers. "We’re not just presenting one therapy for one target. We want to share the platform itself," Li stated. "As long as a receptor for a given cancer antigen has been validated, we can build it into this system and generate T cells specific to that target." This modularity suggests that the platform could be adapted to target a wide array of tumor antigens, potentially expanding the reach of cellular immunotherapies to many solid tumor types that have historically been resistant to treatment.
The development of the AlloESO-T system also benefits from previous manufacturing work conducted by the Yang laboratory for its CAR-NKT platform, another distinct "off-the-shelf" immunotherapy strategy. By leveraging an existing partnership with the UCLA Health Center for Advanced Biotherapies for clinical-grade cell manufacturing, the team expects to accelerate the scaling up of AlloESO-T production. This established infrastructure could significantly expedite the transition of this promising technology from preclinical studies to human clinical trials.
While the preclinical results are highly encouraging and represent a significant leap forward in cancer immunotherapy, it is crucial to note that the therapeutic cells described in this research have not yet undergone testing in human clinical trials. Their safety and efficacy for human use have not been evaluated or approved by regulatory bodies such as the FDA. Future research will focus on advancing these studies to human trials, a critical step required to validate these findings and bring this potentially transformative therapy to patients battling solid tumors.
This pioneering work was supported by contributions from the California Institute for Regenerative Medicine, the UCLA Molecular Biology Institute, the UCLA Office of the Chancellor, and the UCLA Goodman-Luskin Microbiome Center, with additional authors including Jiaji Yu, Yu Jeong Kim, Yanxin Tian, Zhe Li, Yuning Chen, Zibai Lyu, Enbo Zhu, Annabel S. Zhao, Nathan Ma, Catherine Zhang, Adam Kramer, Matthew Wilson, Ryan Hon, Yu-Chen Wang, Siyu Lin, Xinyuan Shen, Zoe Hahn, Yuchong Zhang and Aijun Wang.
About the Author